Two new studies led by researchers at the UCLA Health Jonsson Comprehensive Cancer Center provide new insight into how the immune system can successfully be activated against glioblastoma while revealing why these therapies have historically fallen short.
One study identified features of an effective immune response associated with long-term survival following combination treatment with two immune checkpoint inhibitors, while the other introduced a new preclinical model that more faithfully replicates human glioblastoma, providing a more rigorous platform for developing and testing next-generation treatments.
Glioblastoma is the most aggressive form of brain cancer and remains difficult to treat, with most patients experiencing recurrence despite surgery, radiation and chemotherapy. Unlike many other cancers, glioblastoma has shown limited response to immunotherapy, highlighting the need for a better understanding of how the disease interacts with the immune system.
“For years we've known that immunotherapy works remarkably well in some cancers but has consistently fallen short in glioblastoma, and we've been trying to understand why,” said Robert Prins, PhD, professor of neurosurgery and molecular and medical pharmacology at the David Geffen School of Medicine at UCLA and senior author of both studies. “These studies help explain both sides of that equation. One shows what an effective immune response against glioblastoma looks like in patients, while the other provides a model that faithfully recreates the biology that prevents that response. Together, they give us an unprecedented opportunity to develop and test new therapeutic strategies.”
Combination immunotherapy activates immune system and extends survival in recurrent glioblastoma
The first study, published in Nature Communications, found that giving two immune checkpoint inhibitors, nivolumab and ipilimumab, before surgery stimulated a stronger immune response than nivolumab alone in people with recurrent glioblastoma.
In the phase 2 clinical trial, researchers enrolled 63 patients whose tumors had returned after initial treatment and who were already scheduled for surgery. Participants received either the combination of nivolumab and ipilimumab, nivolumab alone or a placebo before surgery, allowing researchers to analyze tumor tissue removed during the operation and determine how each treatment affected the immune response.
Patients who received the combination therapy lived a median of about 13.5 months, compared with roughly 9 months for those treated with nivolumab alone. Five patients, or about 15% of those who received the combination, became long-term survivors. No long-term responders were observed among patients treated with nivolumab alone.
The combination therapy also triggered significantly greater immune activity within tumors, including increased infiltration of cancer-fighting T cells and higher expression of interferon-related immune genes.
Researchers found that patients whose tumors had the highest T-cell density lived longer, with T-cell density emerging as an independent predictor of overall survival and a potential biomarker for identifying patients most likely to benefit from immunotherapy. The long-term survivors also had substantially higher levels of tumor-infiltrating lymphocytes, further suggesting that T-cell infiltration may be critical to an effective response to immune checkpoint inhibitors.
“These findings give us a clearer picture of what an effective immune response against glioblastoma may look like,” said Lu Sun, adjunct assistant professor of neurosurgery at UCLA and first author of the study. “The long-term survivors showed evidence of a stronger immune response within their tumors, offering important clues for developing treatments that can help more patients benefit from immunotherapy.”
The study also identified early immune changes in the blood that were associated with better outcomes, suggesting blood-based biomarkers could one day help physicians identify which patients are responding to treatment.
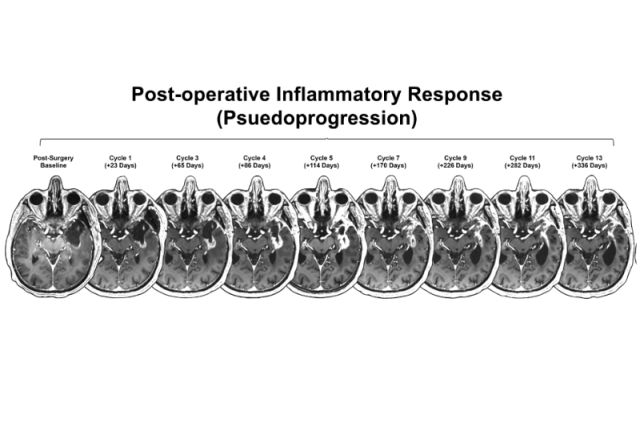
“Several patients treated with dual immune checkpoint blockade showed early pseudoprogression on MRI scans following treatment, which was associated with longer survival,” said Benjamin Ellingson, PhD, director of the UCLA Brain Tumor Imaging Laboratory and professor of radiological sciences. “These findings suggest that early inflammatory changes may occur on imaging in patients that have an effective immune response.”
“This study shows that we can activate the immune system against glioblastoma in ways we have not previously seen,” said co-senior author of the study Timothy Cloughesy, MD, distinguished professor and director of the Neuro-Oncology Program and co-director of the UCLA Brain Tumor Center. “The increase in T cells within the tumor and the association with longer survival give us important clues about what an effective antitumor immune response looks like. Those insights are helping guide the next generation of therapies designed to make immunotherapy work for more patients.”
Preclinical model mirrors human glioblastoma, revealing why immunotherapy falls short
The second study, published in Cancer Research, a journal of the American Association for Cancer Research, describes a new preclinical model of glioblastoma that closely replicates the genetic makeup, biology and immune environment of human disease, providing researchers with a more accurate platform for studying why glioblastoma resists immunotherapy and for testing new treatment strategies.
The model was developed using a technology called MADR (Mosaic Analysis with Dual-Recombinase) that allows scientists to introduce patient-relevant genetic changes into developing brain cells. It was designed around genetic alterations commonly found in human glioblastoma, including EGFRvIII, a cancer-driving mutation that causes continuous activation of the EGFR pathway, along with the loss of tumor suppressor genes PTEN and CDKN2A.
“Unlike commonly used glioblastoma models, which often respond to immune checkpoint inhibitors despite their limited benefit in patients, the new model closely mirrored the biology of human disease,” said David Nathanson, PhD, professor of molecular and medical pharmacology at the David Geffen School of Medicine at UCLA. “The tumors grew diffusely throughout the brain, exhibited the hallmark features of human glioblastoma and developed an immune microenvironment dominated by myeloid cells with very few cancer-fighting T cells, closely resembling what we see in patients.”
Importantly, the model was resistant to immune checkpoint blockade, mirroring the disappointing results seen in clinical trials. Researchers also found that the tumor cells were inherently resistant to T-cell killing and promoted T-cell exhaustion, revealing multiple mechanisms the cancer uses to evade the immune system.
The findings also help explain observations from the Nature Communications study. In patients, tumors with higher T-cell density were associated with longer survival following dual immunotherapy. In contrast, the new preclinical model consistently exhibited very low T-cell infiltration, faithfully recreating the "immune cold" environment that has made glioblastoma so difficult to treat with immunotherapy.
“The tumors have very low T-cell density, which helps explain why they are resistant to immune checkpoint blockade,” said Prins. “Similarly, the MADR model and the clinical study highlight how EGFR alterations are linked to shorter survival and treatment resistance.”
The researchers say the findings from both studies are already guiding the next phase of glioblastoma research. Working with Nathanson and colleagues, the team is investigating whether novel brain-penetrant EGFR inhibitors can create a window of opportunity that makes tumors more susceptible to immunotherapy. In collaboration with Caius Radu, PhD, and his laboratory, the researchers are also developing next-generation mRNA vaccines designed to increase T-cell infiltration into glioblastoma tumors, with the goal of making immunotherapy more effective for more patients.
***
The first author of the Nature Communications paper is Lu Sun, an adjunct assistant professor in the department of neurosurgery at UCLA. Along with Prins and Cloughesy, the other corresponding author is Patrick Wen from Massachusetts General Brigham Cancer Institute. Other UCLA authors are Lauren Markus, Julio Sanchez, Thomas Lai, Gang Li, Jiyoon Kim, Richard Everson and Benjamin Ellingson.
The co-first authors of the Cancer Research paper are Katie Grausam from Cedars-Sinai and Marissa Pioso and Julio Sanchez from UCLA. Along with Prins, the senior authors are David Nathanson from UCLA and Joshua Breunig and Stephen Shiao from Cedars-Sinai. Other UCLA authors are Marissa Li, Gilbert Herrera, Thomas Lai, Trinh Phan, Sophie Ashley, Ariel Andrade, Lauren Markus, Jingwen Yao and Linda Liau.